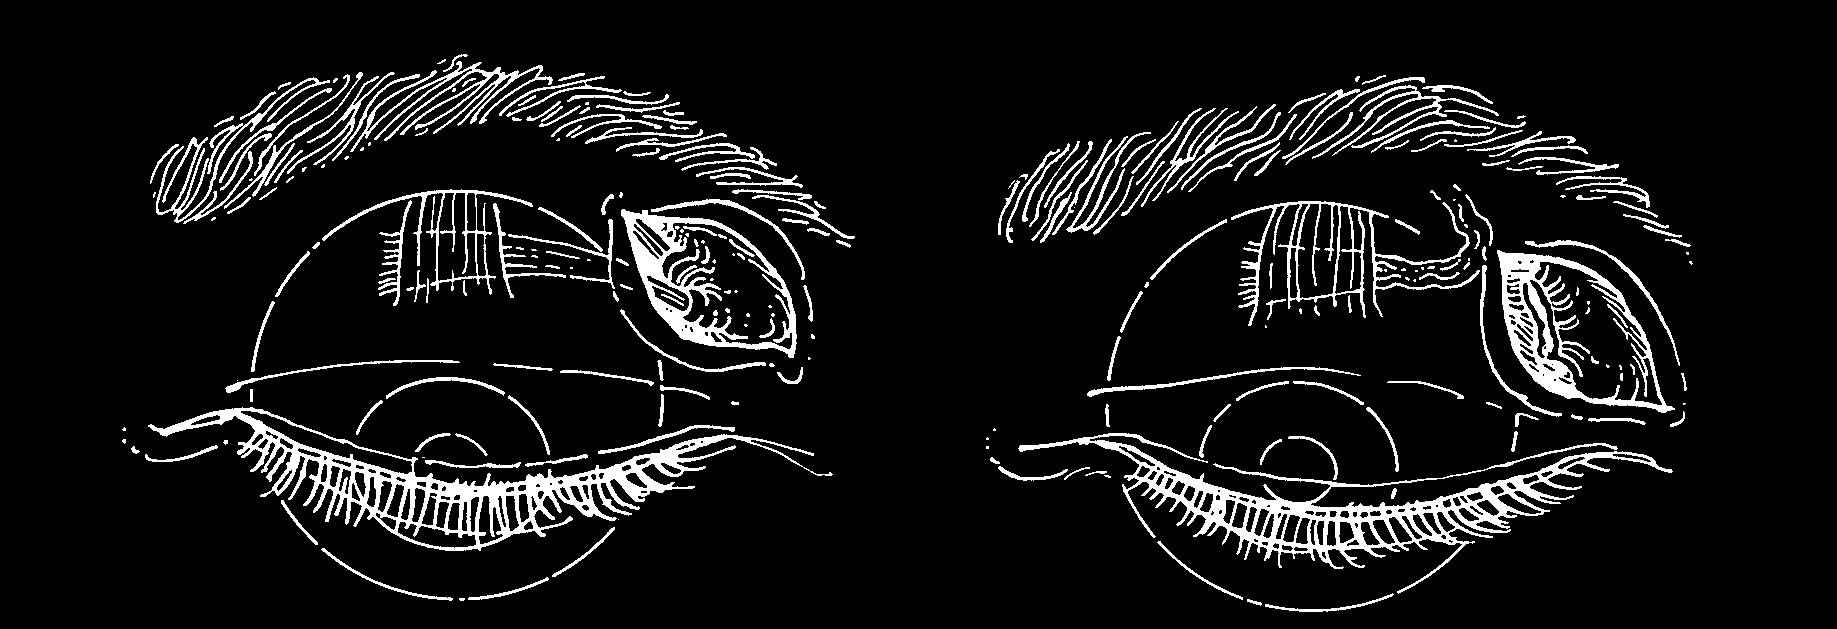
Figure 18
Hughes and Bogart exposed the trochlea subperiosteally, freed it, and pushed it backward several millimeters to weaken the superior oblique. This formidable procedure was accomplished with a transcutaneous approach. No reports of series of patients having this procedure performed on them were described. It is unlikely that his procedure was done widely; it indicates the imagination and ingenuity of the early strabismus surgeon. This procedure, when performed inadvertently after use of the Lynch incision for exposure of the ethmoid sinus, can produce superior oblique underaction, creating the clinical picture of superior oblique palsy which, in turn, results in diplopia for the unlucky patient.
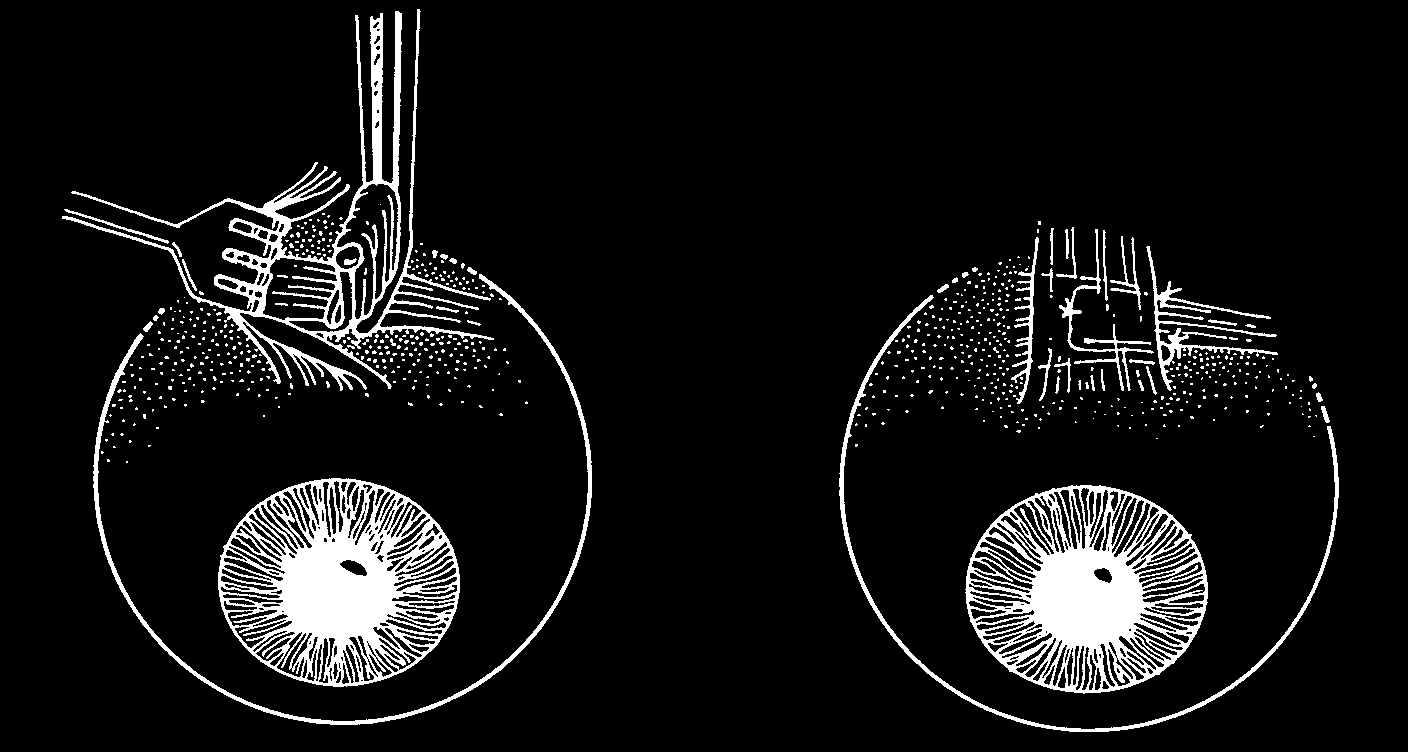
Figure 19
White plicated the superior oblique tendon medial to the superior rectus using a tucking instrument. He advised placing the tuck nearer the superior rectus and away from the ‘pulley’ of the trochlea to avoid having the superior oblique tendon become hung up in the trochlea.
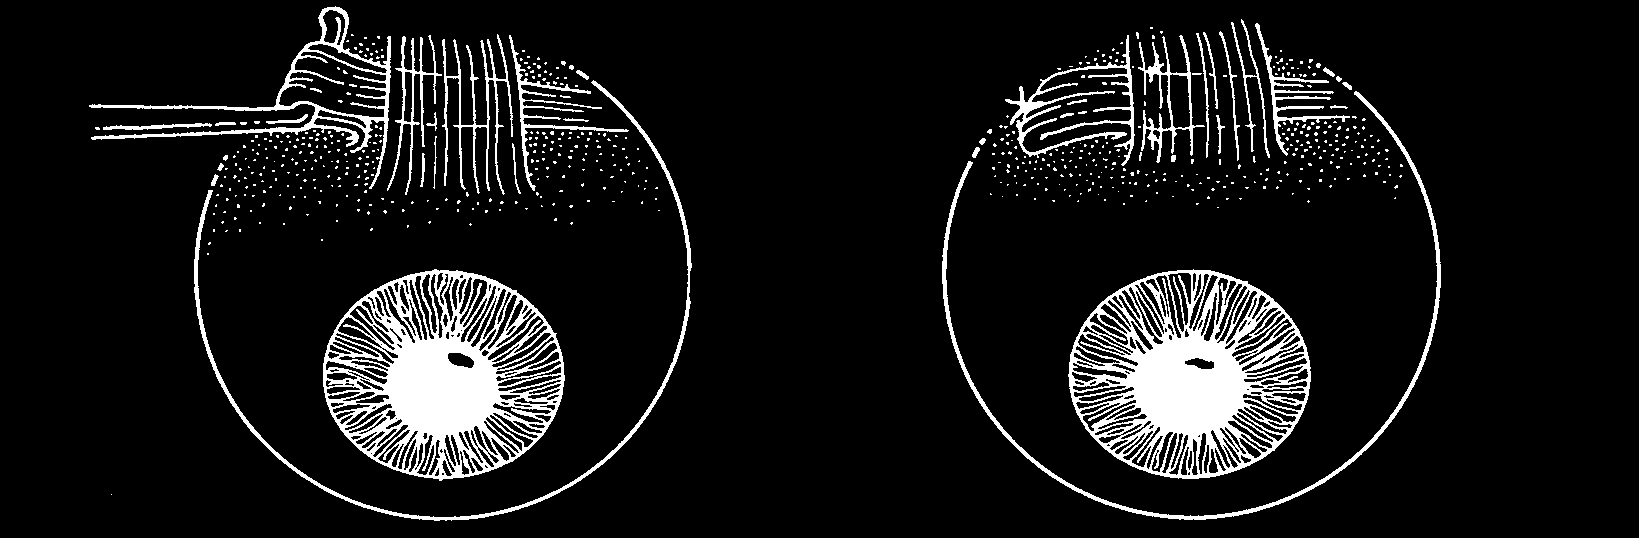
Figure 20
McLean engaged the superior oblique tendon temporally and brought the redundant loop of tendon temporally. This technique for tucking the superior oblique tendon was said to reduce the incidence of postoperative limitation of elevation in adduction by avoiding the trochlea and by reducing the likelihood of adherence of the redundant loop of tendon to the superior rectus. However, any superior oblique tuck will cause a Brown postoperatively unless the tuck is done in a loose tendon and will result postoperatively in an equal and normal superior oblique traction test (see chapter 9).
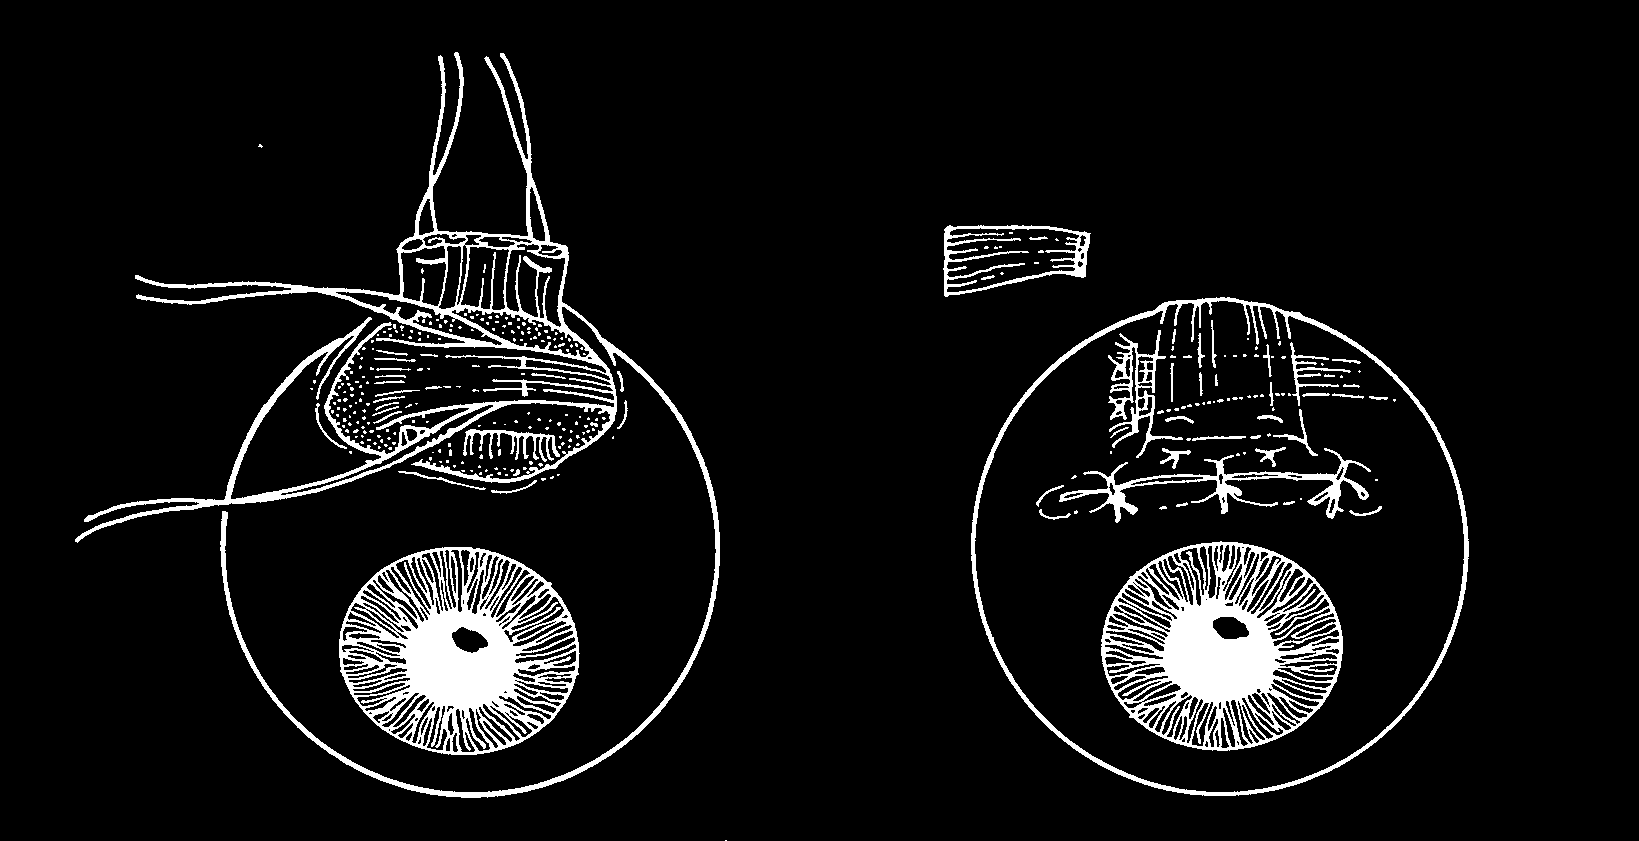
Figure 21
Based on a procedure originally suggested by McGuire, Fink described resection of the superior oblique tendon after detaching the superior rectus muscle. Removal of the superior rectus provided improved exposure of the superior oblique tendon.
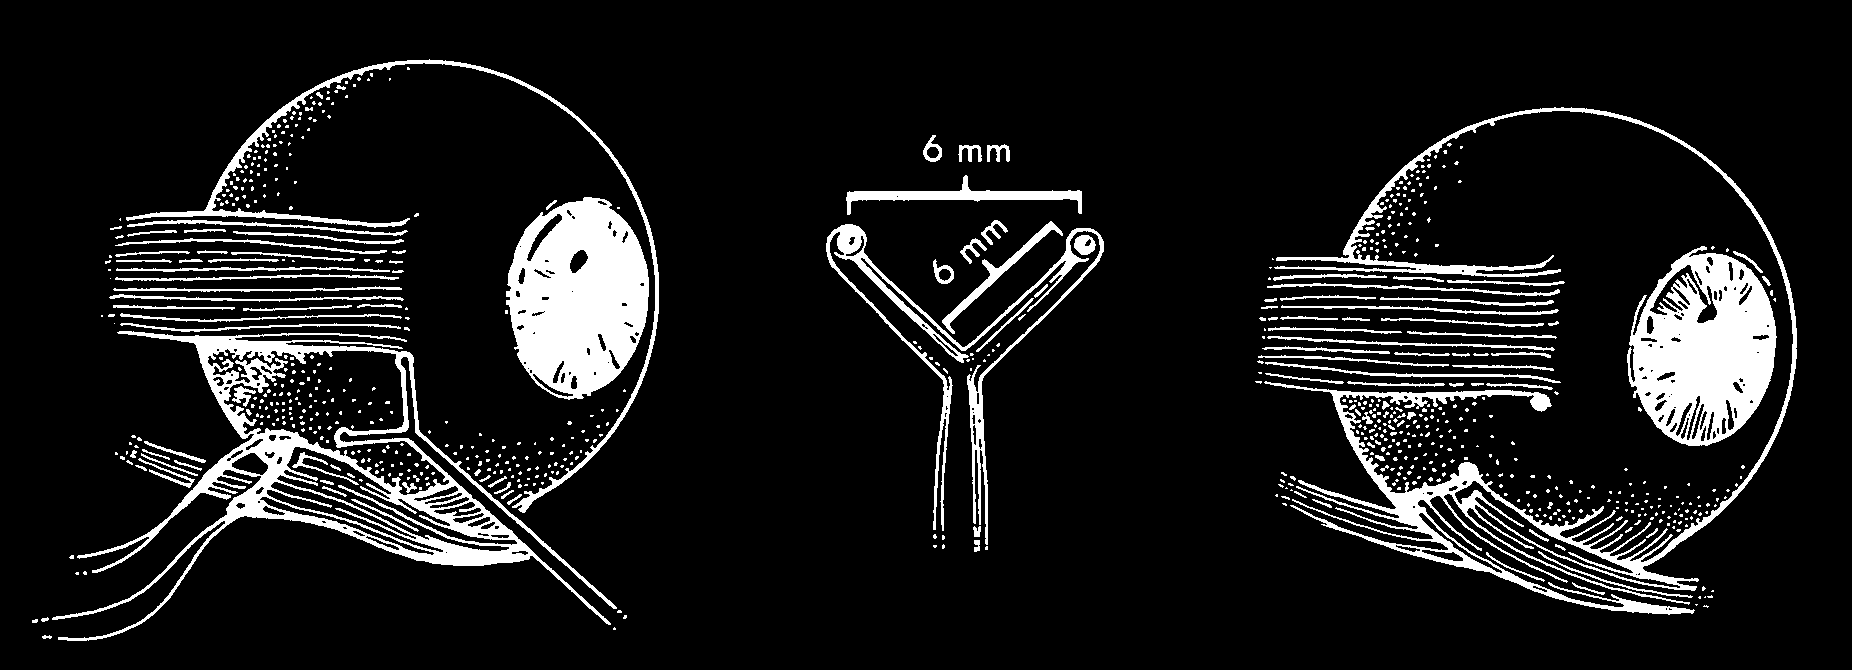
Figure 22
Fink recessed the inferior oblique muscle using a recession localizer that had a 7 cm handle with 6 mm arms projecting at 90 degrees from each other and a 1 mm tip with a concavity to hold gentian violet for marking. The purpose of the instrument was to allow for an accurate 8.0 mm recession of the inferior oblique muscle. By estimation the recession could be reduced to 6.0 mm or increased to 10.0 mm.

Figure 23
Following the lead of Duane, White and Brown weakened the inferior oblique by disinsertion without reattachment, considering the procedure safe and effective.
A
B1
B2
C
D
E
F
G
H
I
J
K