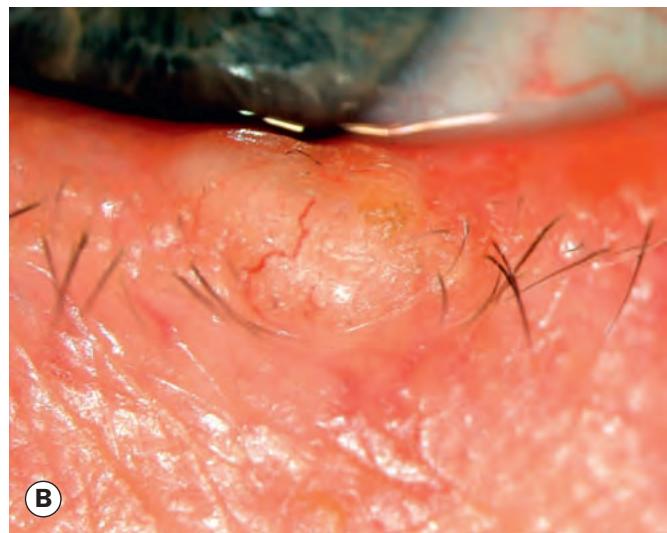
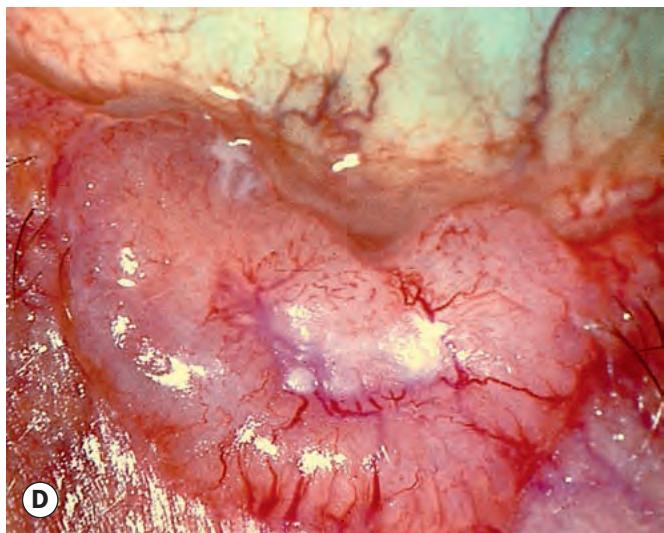

Fig. 1.19 Clinical appearance of basal cell carcinoma. (A) Early nodular lesion; (B) larger nodular tumour; (C) rodent ulcer; (D) large rodent ulcer;
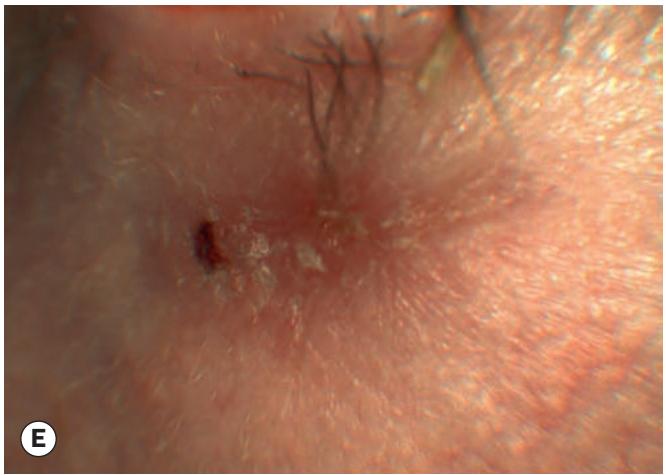
Fig. 1.19, Continued (E) sclerosing tumour; (F) extensive sclerosing tumour

the epidermis as an indurated plaque (Figs 1.19E and F). The margins of the tumour may be impossible to delineate clinically and the lesion tends to be much more extensive on palpation than inspection. On cursory examination a sclerosing BCC may simulate a localized area of chronic blepharitis.
Other types not usually found on the lid are cystic, adenoid, pigmented and multiple superficial.
Squamous cell carcinoma
Introduction
SCC is a much less common, but typically more aggressive tumour than BCC with metastasis to regional lymph nodes in about 20% of cases. Careful surveillance of regional lymph nodes is therefore an important aspect of initial management. The tumour may also exhibit perineural spread to the intracranial cavity via the orbit. SCC accounts for 5–10% of eyelid malignancies and may arise de novo or from pre-existing actinic keratosis or carcinoma in situ (Bowen disease, intraepidermal carcinoma – Fig. 1.20). Immunocompromised patients, such as those with acquired immunodeficiency syndrome (AIDS) or following renal transplantation are at increased risk, as are those with a predisposing syndrome such as xeroderma pigmentosum. The tumour has a predilection for the lower eyelid and the lid margin. It occurs most commonly in older individuals with a fair complexion and a history of chronic sun exposure. The diagnosis of SCC may be difficult because certain ostensibly benign lesions such as keratoacanthoma and cutaneous horn may reveal histological evidence of invasive SCC at deeper levels of sectioning.
Histopathology
The tumour arises from the squamous cell layer of the epidermis. It is composed of variably sized groups of atypical epithelial cells with prominent nuclei and abundant eosinophilic cytoplasm within the dermis (Fig. 1.21A). Well-differentiated tumours may show characteristic keratin ‘pearls’ and intercellular bridges (desmosomes).
Clinical features
The clinical types are variable and there are no pathognomonic characteristics. The tumour may be indistinguishable clinically from a BCC but surface vascularization is usually absent, growth is more rapid and hyperkeratosis is more common.
Nodular SCC is characterized by a hyperkeratotic nodule that may develop crusting, erosions and fissures (Fig. 1.21B).
Ulcerating SCC has a red base and sharply defined, indurated and everted borders, but pearly margins and telangiectasia are not usually present (Fig. 1.21C).
Cutaneous horn with underlying invasive SCC (Fig. 1.21D).
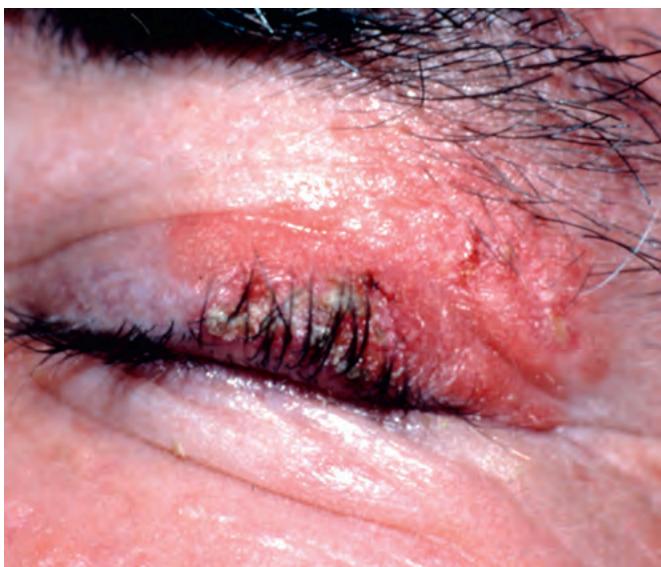
Fig. 1.20 Carcinoma in situ
(Courtesy of H Frank)